
Adult Deformity
Ultrasound examination of the erector spinae muscle in patients with thoracic scoliosis after dynamic and rigid fixation
- N.N. Priorov National Medical Research Center, Moscow, Russia
Abstract
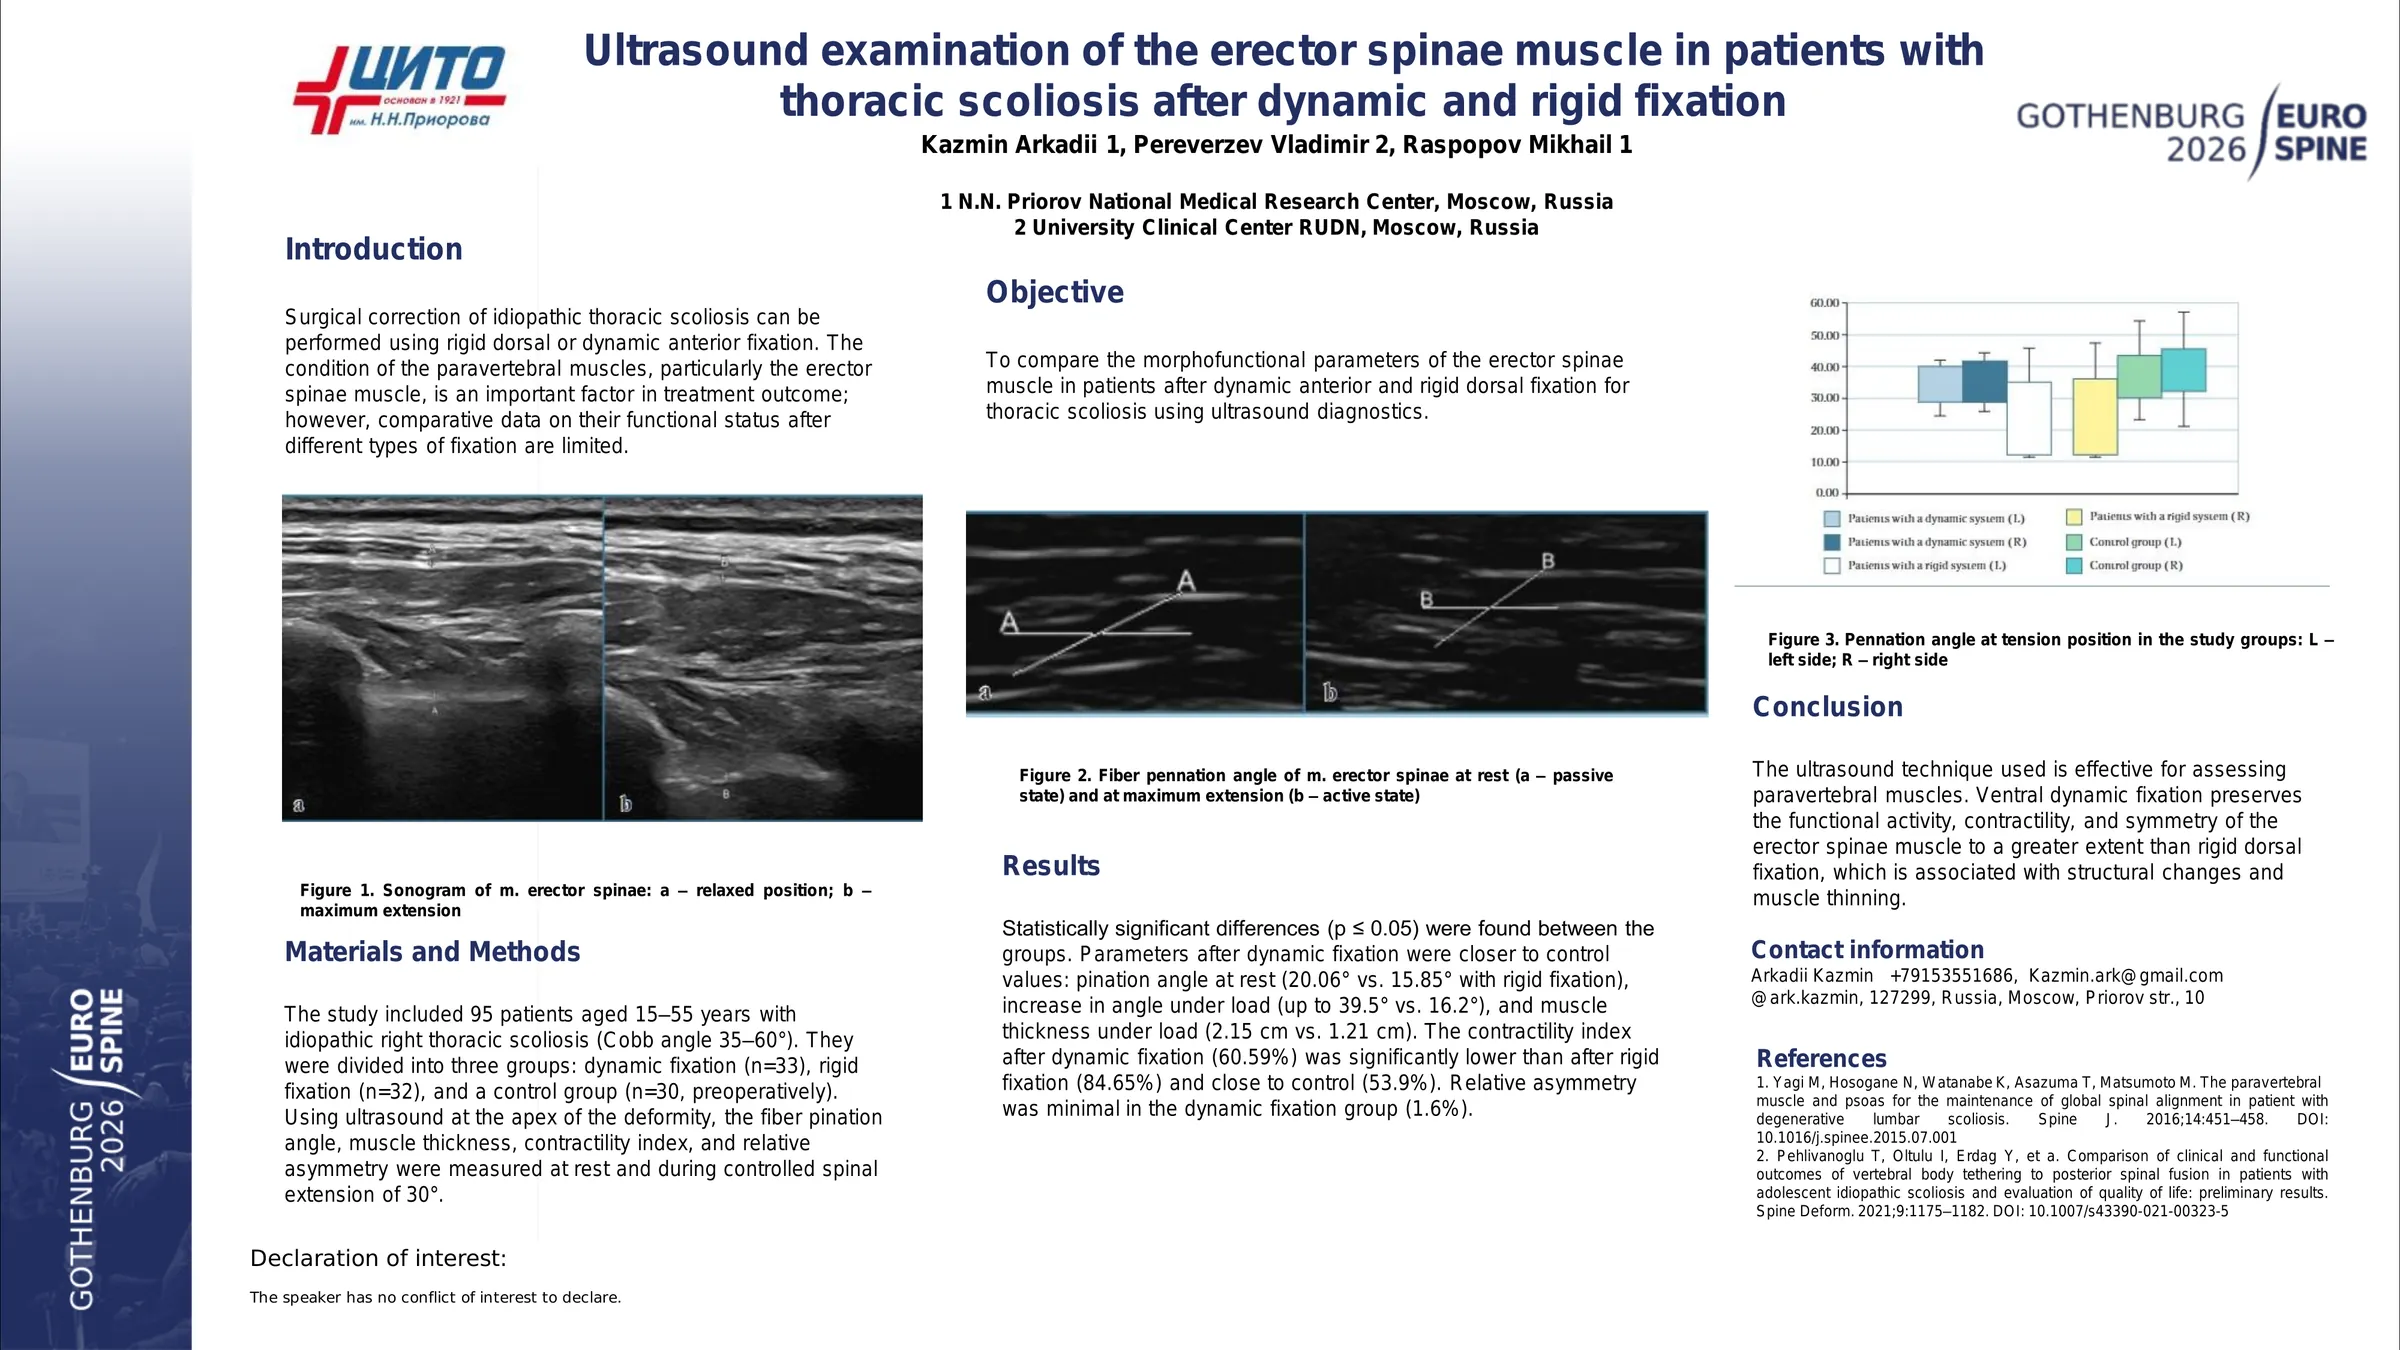
Surgical correction of idiopathic thoracic scoliosis can be performed using rigid dorsal or dynamic anterior fixation. The condition of the paravertebral muscles, particularly the erector spinae muscle, is an important factor in treatment outcome; however, comparative data on their functional status after different types of fixation are limited.
Objective - to compare the morphofunctional parameters of the erector spinae muscle in patients after dynamic anterior and rigid dorsal fixation for thoracic scoliosis using ultrasound diagnostics
The study included 95 patients aged 15–55 years with idiopathic right thoracic scoliosis (Cobb angle 35–60°). They were divided into three groups: dynamic fixation (n=33), rigid fixation (n=32), and a control group (n=30, preoperatively). Using ultrasound at the apex of the deformity, the fiber pination angle, muscle thickness, contractility index, and relative asymmetry were measured at rest and during controlled spinal extension of 30°
Statistically significant differences (p ≤ 0.05) were found between the groups. Parameters after dynamic fixation were closer to control values: pination angle at rest (20.06° vs. 15.85° with rigid fixation), increase in angle under load (up to 39.5° vs. 16.2°), and muscle thickness under load (2.15 cm vs. 1.21 cm). The contractility index after dynamic fixation (60.59%) was significantly lower than after rigid fixation (84.65%) and close to control (53.9%). Relative asymmetry was minimal in the dynamic fixation group (1.6%)
The ultrasound technique used is effective for assessing paravertebral muscles. Ventral dynamic fixation preserves the functional activity, contractility, and symmetry of the erector spinae muscle to a greater extent than rigid dorsal fixation, which is associated with structural changes and muscle thinning